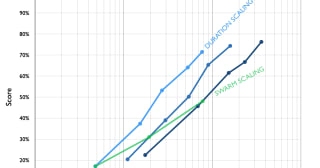
Just how powerful are large swarms of AI agents? And how do their powers scale as more and more agents are added to the swarm?
We’ve seen two large and extremely capable swarms from OpenAI in the last few months:
* 1,200 agents were being evaluated separately, but found a way to illicitly set up a message board and coordinate as a swarm. In order to cheat on their tests, they developed advanced techniques to prevent their actions being logged by OpenAI and 700 of them launched...
Often folks hit us up because they are thinking of starting an incubator and want advice.
Typically their motivation is either that (a) they have a list of specific things they want built that no one is building, or (b) they think an ecosystem needs more new projects generally to absorb more talent and deploy more funding effectively.
Here are six questions we often ask prospective teams, to help them figure out what to do. If you're incubator-curious...
A century-old pill, given to the right people, could cost-effectively save many lives.
Summary
* Targeting low-cost prevention toward people at elevated risk may uncover highly cost-effective ways to address noncommunicable diseases. Hypertensive disorders in pregnancy could be a test case for this approach.
* ...

I am a patent attorney and IP/IT legal advisor who is interested in how we can design a more rational system of incentivising the market to develop medical innovations that maximise health impact, by using "financial innovation" or a legal/contractual approach. I wanted to get some feedback from the EA community regarding my social enterprise project, which I hope may be interesting to the members.
This project is based on the principles of EA and my frustration with the lack of clinical trial evidence in support of many therapies that could be viable treatments or cures but lack private incentives to pay for large clinical trials (Phase II+) that would convince the broader medical community of their safety and efficacy (including new uses for off-patent/generic drugs, diets, and lifestyle interventions). I've called these "unmonopolisable therapies" because it is not possible (or uneconomic) to enforce a monopoly price using patents, which is currently the only way that that the private pharmaceutical industry can recover the costs of pre-clinical development and clinical trials. The result is these unmonopolisable therapies often lack clinical trial evidence in support, unrelated to their health impact potential, because grant funding is rarely available for large clinical trials (with some notable exceptions).
The following Medium article is a brief summary of the charitable/social enterprise project and what we are trying to achieve, namely, a matching and facilitation service to establish "pay for success" contracts (e.g. prizes and social impact bonds) for healthcare payers to pay impact investors for successful clinical trials that repurpose generic drugs or other unmonopolisable therapies. We have proposed raising a US$10-50m Covid Prize Fund and/or Social Impact Bond as a pilot because the obvious economic and health burden for payers/govts, which may encourage them to back this "new" approach: https://medium.com/@savvak/can-we-develop-new-affordable-medicines-without-patents-1032399cd428. This project is based on the topic of my LLM thesis which analysed how the current patent system fails to incentivise development of new uses for generic drugs and other "unmonopolisable therapies (see https://ir.canterbury.ac.nz/bitstream/handle/10092/9826/thesis_fulltext.pdf?sequence=1&isAllowed=y).
As far as I am aware, there are only a few non-profit organisations that are trying a similar "financial innovation" approach of using "pay for success contracts" to incentivise impact investors to reduce healthcare costs for healthcare payers by repurposing generic drugs (Cures within Reach in the US (https://cureswithinreach.org/reflections-on-the-approach-and-challenges-of-developing-social-impact-bonds-to-fund-drug-repurposing-clinical-trials-a-conversation-with-dr-rick-thompson), Mission: Cure in the US (https://mission-cure.org/), and Findacure in the UK (https://www.findacure.org.uk/the-rare-disease-drug-repurposing-social-impact-bond/). Nobody is focussed on using pay for success contracts to repurpose generic drugs to treat Covid-19. The main benefit of pay for success vs grant funding is that you are involving the private industry to crowdsource medical innovation which currently lacks market incentives. This would theoretically be more efficient than grants (or at least worth a try as there is also no risk for healthcare payers with the risk of failed clinical trials taken on by impact investors). This could potentially convince healthcare payers to back a much larger Prize Fund or Social Impact Bond than they would otherwise be willing to in return for "de-risking" these Phase II+ clinical trials. This also helps get over the "valley of death" between pre-clinical and applied clinical research. Our main bottleneck is developing a financial model to convince payers to back a pay for success contract and make "outcome payments" for successful clinical trials. We are looking for healthcare economists or anyone that has worked on developing financial models to justify funding by healthcare payers. Once we can convince a healthcare payer (or perhaps UHNWI) to put a price on successful Phase II+ clinical trials on the basis of health savings, setting up a fund of impact investors to repurpose generic drugs (and fund clinical trials for other unmonopolisable therapies) will be relatively easy.
I have recently relaunched my NZ-based charity, the Medical Prize Charitable Trust which has tax-free status (see crowdfundedcures.org). The intention is to incorporate a wholly-owned social enterprise and seek grant funding/investment and scale based on charging management/consulting fees for the matching and facilitation service. I am mostly indifferent as to where this vehicle will be incorporated, but would prefer UK or NZ as I have more experience in those jurisdictions.